
Verified
I took one tablet with dinner. The first week brought loose stools, mostly when dinner was small. After changing to a proper evening meal, that settled. My fasting readings improved gradually rather than overnight.
6 Sep 2026

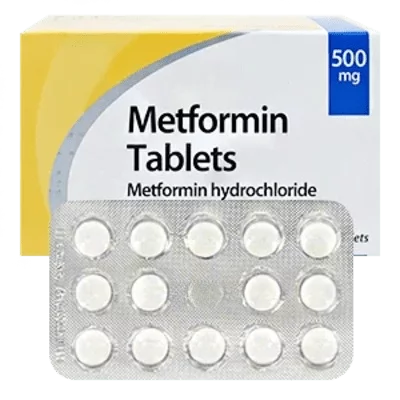
Metformin is an oral tablet for adults with type 2 diabetes and selected people with insulin resistance or polycystic ovary syndrome. It helps lower blood glucose by reducing glucose release from the liver and improving the body’s response to insulin. The dose is stated on the pack — follow the leaflet.
The dose is stated on the pack — follow the leaflet. Metformin belongs to the biguanide class of glucose-lowering medicines and has been included in the WHO Model List of Essential Medicines because of its established role in type 2 diabetes care [1].
Metformin does not force the pancreas to release extra insulin. This distinction matters because, when used alone, it has a low risk of causing hypoglycaemia.
Metformin is commonly used for:
Metformin is taken orally as a tablet. The dose is stated on the pack — follow the leaflet. The final dose depends on glucose results, kidney function, other diabetes medicines, and the treatment goal.
FDA prescribing information for metformin supports gradual dose titration because slower increases can reduce gastrointestinal adverse effects [2].
People sometimes stop treatment after one episode of diarrhoea. A better clinical approach is to identify whether the tablet was taken without food, whether the dose was increased too quickly, or whether an intercurrent stomach infection was present.
Metformin acts mainly in the liver, where it reduces hepatic gluconeogenesis, the process by which the liver produces glucose. It also improves insulin sensitivity in muscle and fat tissue, helping the body use circulating glucose more efficiently. Metformin does not work like insulin; it helps the body use its own insulin better.
Metformin is commonly used for:
Metformin is often the starting medicine for type 2 diabetes, though the right treatment can change when kidney disease, heart failure, established cardiovascular disease, or marked hyperglycaemia is present.
| Treatment approach | Main action | Practical distinction |
|---|---|---|
| Metformin | Reduces liver glucose production and improves insulin sensitivity | Low hypoglycaemia risk alone; gastrointestinal effects are common early on |
| Sulfonylurea medicines | Stimulate pancreatic insulin release | Can lower glucose quickly but may cause hypoglycaemia and weight gain |
| GLP-1 receptor agonist medicines | Increase glucose-dependent insulin release and reduce appetite | Often useful when weight reduction is a major goal; nausea can occur |
Metformin is usually preferred when insulin resistance is a central feature and kidney function permits treatment. Sulfonylureas can be useful where a stronger immediate glucose-lowering effect is needed, though low blood glucose becomes more likely. GLP-1 receptor agonist treatment may suit people who also need significant weight management or cardiovascular risk reduction.
Combination therapy is common. Metformin may be used with insulin, SGLT2 inhibitors, GLP-1 receptor agonists, DPP-4 inhibitors, or sulfonylureas, though the monitoring needs differ with each combination.
Metformin is not for you if you have severe kidney impairment with an estimated glomerular filtration rate below 30 mL/min/1.73 m², acute metabolic acidosis, diabetic ketoacidosis, or a known allergy to metformin.
The European Medicines Agency advises renal-function-based use of metformin, including dose adjustment or stopping treatment when kidney function is significantly reduced [3].
Iodinated contrast can temporarily affect kidney function. Metformin may need to be paused around certain scans and restarted only after renal function is judged suitable.
Metformin itself does not usually cause low blood glucose. The risk changes when it is combined with insulin or insulin-releasing medicines. Alcohol can also increase the chance of low glucose and raises concern for lactic acidosis when intake is heavy or accompanied by poor nutrition.
Talk to a clinician before using Metformin if you have serious kidney problems, severe illness, significant liver disease, heart or breathing failure, or an infection. You should also seek advice if you are dehydrated from vomiting or diarrhoea, drink heavily, are planning major surgery, or are due to have a scan using iodinated contrast material.
Digestive symptoms are the main limitation of Metformin. Nausea, diarrhoea, stomach discomfort, reduced appetite, flatulence, and a metallic taste can occur, especially at the start of treatment or after a dose increase.
For many people, symptoms ease after the body adjusts. Persistent symptoms deserve attention because they can affect food intake, hydration, and adherence.
Long-term metformin use can reduce vitamin B12 absorption. This may contribute to tiredness, sore tongue, tingling, numbness, or worsening neuropathy in susceptible people. Blood testing is often considered when these symptoms appear or when treatment has continued for years.
A rare but serious complication is lactic acidosis, in which lactate accumulates in the blood. The risk rises with severe kidney impairment, major dehydration, uncontrolled heart or breathing failure, severe infection, or excessive alcohol intake. Urgent assessment is needed for unusual muscle pain, severe weakness, rapid breathing, persistent vomiting, or extreme drowsiness.
Several avoidable habits make Metformin harder to tolerate or less useful.
In clinical practice, doctors often value Metformin because it addresses insulin resistance without routinely causing hypoglycaemia when used on its own. They also expect the first weeks to require patience. The medicine works best when dose escalation is measured rather than rushed.
Clinicians usually review three practical areas: glucose trends, kidney function, and tolerability. A normal glucose reading after a few days does not settle the long-term plan, while persistent gastrointestinal symptoms can often be improved by changing timing, dose progression, or the formulation used.
Kidney function is not a background detail. It directly affects whether Metformin can be continued and at what dose.
For people with type 2 diabetes, doctors also look beyond glucose. Blood pressure, cholesterol, body weight, cardiovascular disease, kidney disease, smoking status, and other medicines influence the treatment plan.
Metformin begins affecting glucose handling after treatment starts, though the meaningful clinical response is usually assessed over several weeks. Dose increases are often spaced out to improve tolerability and to see how glucose readings respond. The American Diabetes Association’s 2025 Standards of Care supports individualised review using glucose results and broader health risks rather than judging treatment from a few early readings. HbA1c is commonly rechecked after roughly three months because it reflects average glucose over time. Clinicians may also review treatment sooner when readings remain high or symptoms develop.
Metformin alone rarely causes hypoglycaemia because it does not directly trigger insulin release. Low glucose becomes more possible when it is combined with insulin or a sulfonylurea medicine, when meals are skipped, or after prolonged physical exertion. Symptoms can include sweating, tremor, hunger, palpitations, dizziness, or confusion. WHO diabetes guidance published in 2023 distinguishes metformin from medicines that more directly raise hypoglycaemia risk.
Metformin may be prescribed for selected people with polycystic ovary syndrome, mainly when insulin resistance, impaired glucose tolerance, or type 2 diabetes is present. It can improve metabolic markers and may support more regular ovulation for some people, though responses differ. The 2023 International Evidence-based Guideline for PCOS, developed by Monash University and international partners, places lifestyle measures and individual risk assessment at the centre of care. Treatment decisions also depend on fertility goals, menstrual symptoms, body weight, and glucose results.
The kidneys remove metformin from the body. Reduced kidney function can allow the medicine to accumulate, increasing the risk of lactic acidosis during severe illness or dehydration. EMA guidance issued in 2016 recommends using estimated glomerular filtration rate to guide dosing and contraindications. Testing frequency depends on age, baseline kidney function, and conditions that may affect the kidneys.
Long-term treatment may reduce vitamin B12 absorption in some people. The risk is more relevant when treatment continues for years or when dietary intake and absorption are already limited. The Medicines and Healthcare products Regulatory Agency (MHRA) updated its metformin safety advice in 2022 to describe low vitamin B12 as a common adverse effect and to encourage testing when symptoms suggest deficiency. Tingling, numbness, sore tongue, unexplained fatigue, and anaemia merit clinical assessment.
Vomiting, diarrhoea, fever, and poor fluid intake can cause dehydration, which may temporarily increase metformin-related risk. Many clinical sick-day plans advise pausing metformin during significant dehydration and resuming once normal eating and drinking have returned. NICE guidance updated in 2022 supports individualised diabetes management during acute illness, especially where kidney function may be affected. A person using insulin should not stop insulin without a clear clinical plan.
Your order will be securely packed and shipped within 24 hours. This is exactly what your package will look like (images of an actual item sent). It has the size and look of a regular private letter (9.4x4.3x0.3 in. or 24x11x0.7 cm) and its contents cannot be seen.
I took one tablet with dinner. The first week brought loose stools, mostly when dinner was small. After changing to a proper evening meal, that settled. My fasting readings improved gradually rather than overnight.
I was prescribed it for insulin resistance linked to PCOS. I had a metallic taste for about ten days and less appetite at first. By the second month, I found it easier to stay consistent with meals.
The medicine lowered my readings, but I made the mistake of taking it after tea instead of food. Stomach cramps were annoying until my dose schedule was adjusted. I also learned not to skip my kidney blood tests.
The glucose numbers moved in the right direction, but diarrhoea did not settle for me after several weeks. My prescriber changed the plan rather than asking me to push through it.
